




Zero trust is a security philosophy until it's tied to actual access decisions. Here's how to make it satisfy HIPAA's Security Rule instead of just describing it.
A mindset doesn't pass an OCR audit.
Zero trust gets pitched as "never trust, always verify," and that's accurate as far as it goes. But what satisfies HIPAA's access control requirements isn't the principle. It's what the principle looks like once it's implemented as access decisions: least privilege enforced by default, every request re-verified regardless of network location, and continuous review of who still needs access to what. Those are the controls a user access review program and lifecycle automation enforce together.
This article skips the zero trust theory and goes straight to the access control mechanics that make it work for protected health information. In it, we cover where zero trust meets the Security Rule, the three principles that are actually enforceable, the four mechanics that turn them into controls, and what the result looks like as audit evidence.
Where Zero Trust Meets HIPAA's Security Rule
HIPAA's Security Rule requires administrative, physical, and technical safeguards for ePHI. The technical safeguards are where zero trust applies most directly: unique user identification, role-based access restriction, and audit controls that track who accessed PHI and when.
Traditional perimeter security assumes anyone inside the network is trustworthy. That assumption doesn't survive a cloud-first environment where PHI moves across dozens of SaaS applications, remote employees, and third-party integrations. Zero trust replaces the assumption with a rule: every request for PHI, wherever it originates, is verified against least privilege before it's granted.
The prose version of how the Security Rule's technical safeguards line up with zero trust, then the table: unique user identification maps to per-identity verification on every request; access restriction maps to least privilege scoped by role; and audit controls map to the continuous logging and review that zero trust requires anyway.

Zero trust strengthens your ability to meet the Privacy and Security Rules. Breach notification to affected individuals and HHS remains the organization's responsibility; no access control model handles that step.
The Three Access Control Principles That Matter
Strip zero trust down to what's actually enforceable, and it comes to three things.
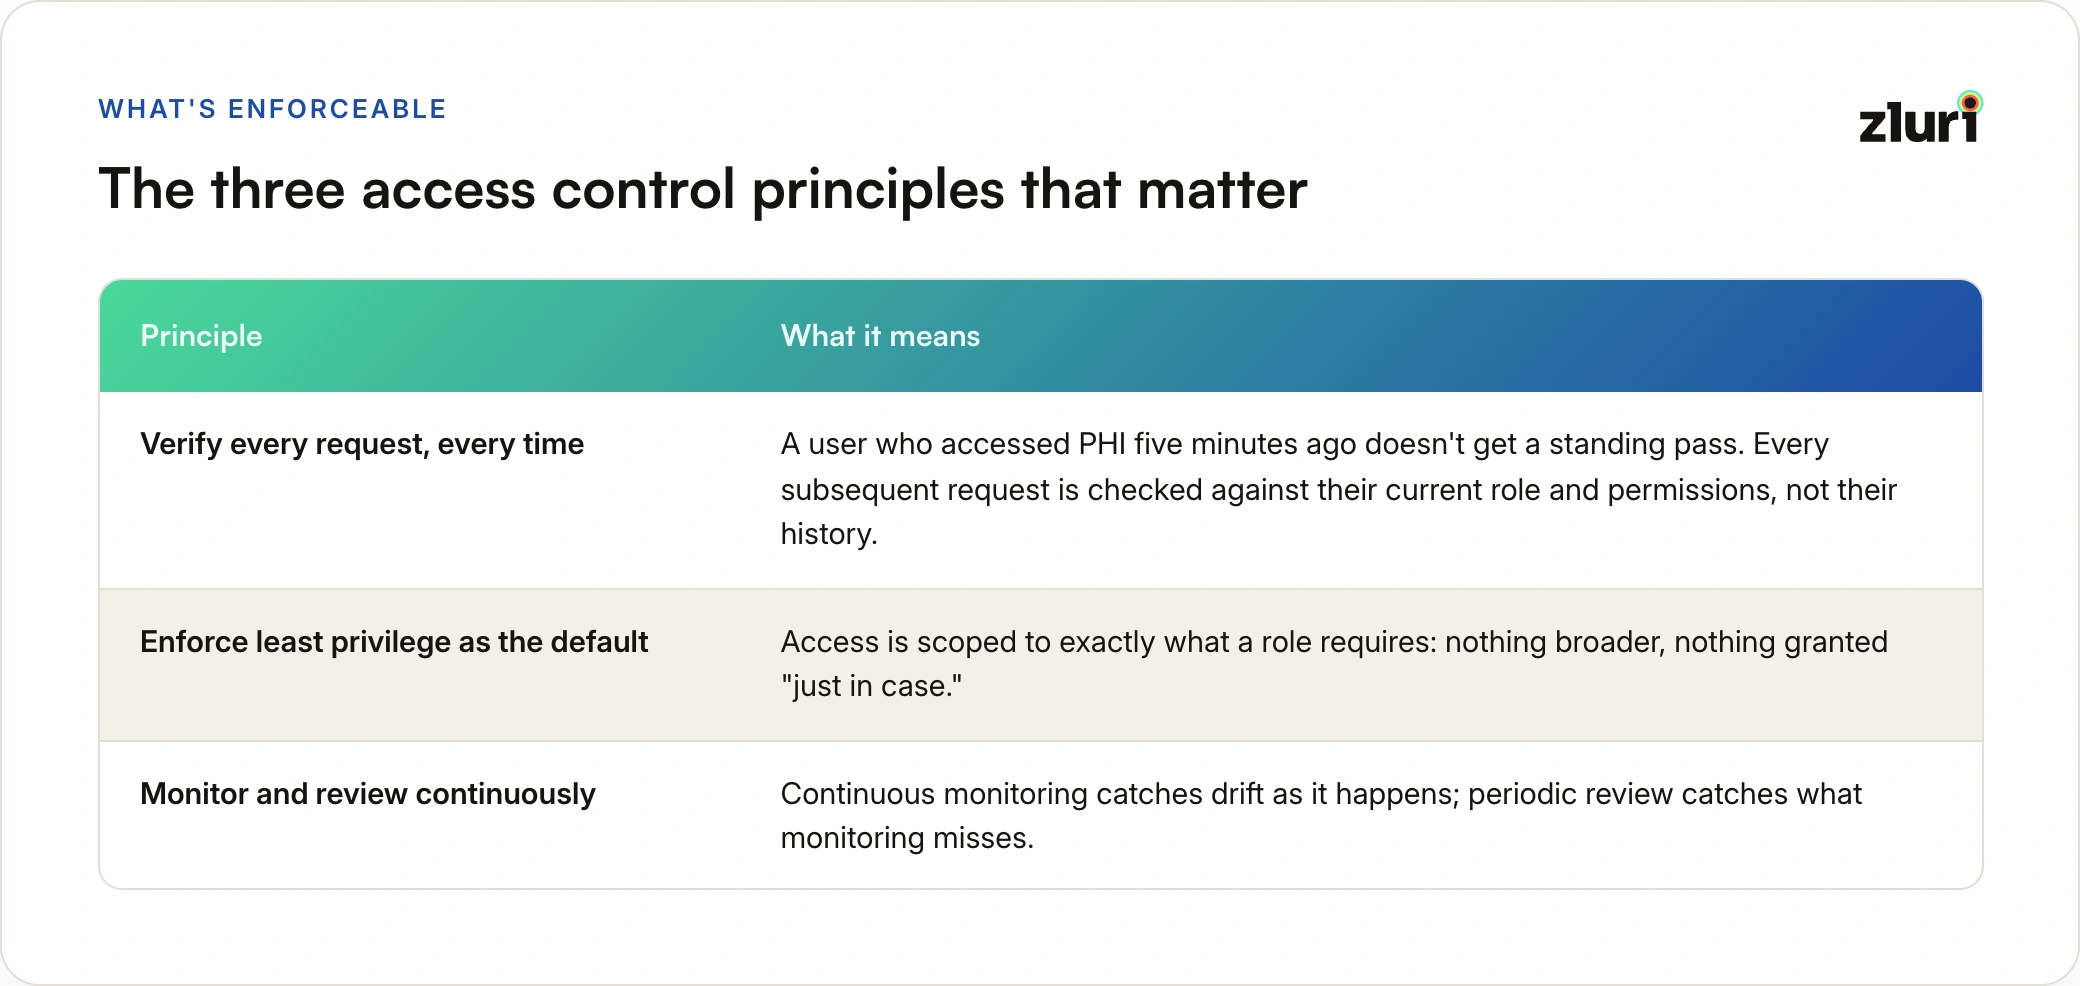
- Verify every request, every time. A user who accessed PHI five minutes ago doesn't get a standing pass. Every subsequent request is checked against their current role and permissions, not their history.
- Enforce least privilege as the default. Access is scoped to exactly what a role requires: nothing broader, nothing granted "just in case." The principle of least privilege is the oldest rule in access control, and the one that fails most often in practice because it's stated as policy rather than enforced as default.
- Monitor and review continuously. Access that was correct on day one can be wrong by day ninety. Continuous monitoring catches drift as it happens; periodic review catches what monitoring misses.
Each of these maps to a specific access control mechanism, not a policy statement. That's the part most zero trust write-ups skip, and it's the part that follows.
Turning the Principles Into Access Control
1. Classify Applications by PHI Exposure
Before enforcing anything, know where PHI actually lives.
Inventory every application in your environment, flag the ones that store, process, or transmit PHI, and rank them by sensitivity. This determines where to concentrate access control effort first, rather than applying the same scrutiny everywhere. It also exposes the applications that handle PHI without anyone having classified them that way: departmental tools adopted outside IT, integrations that pull patient data into a workflow platform, and vendor systems with standing access.
The classification doubles as the scope definition for everything downstream. The applications ranked highest are where per-application boundaries, tightest role scoping, and most frequent review should land. Our HIPAA access control checklist covers the inventory step in more depth.
2. Replace the Network Perimeter With Per-Application Access Control
Instead of one broad perimeter, treat each PHI-handling application as its own access boundary.
A request from inside the corporate network gets the same verification as a request from outside it. This does two things. It removes the implicit trust that network location used to confer, which is the core zero trust move. And it limits the identity blast radius: if one application is compromised, the access boundary around it stops the compromise from reaching the next one.
For PHI specifically, this means a clinician's access to the EHR says nothing about their access to the billing platform, the imaging system, or the patient communication tool. Each is granted, verified, and reviewed on its own terms.
3. Automate Role-Based Access and Lifecycle Events
This is where zero trust either becomes real or stays theoretical.
Manually configuring least privilege for every role, across every application, and keeping it current as people join, change roles, and leave does not scale past a handful of systems. In healthcare environments, where workforce turnover is high, roles are specialized, and contractors and locum staff cycle through constantly, the manual version fails fast.
The failure concentrates on three lifecycle events:
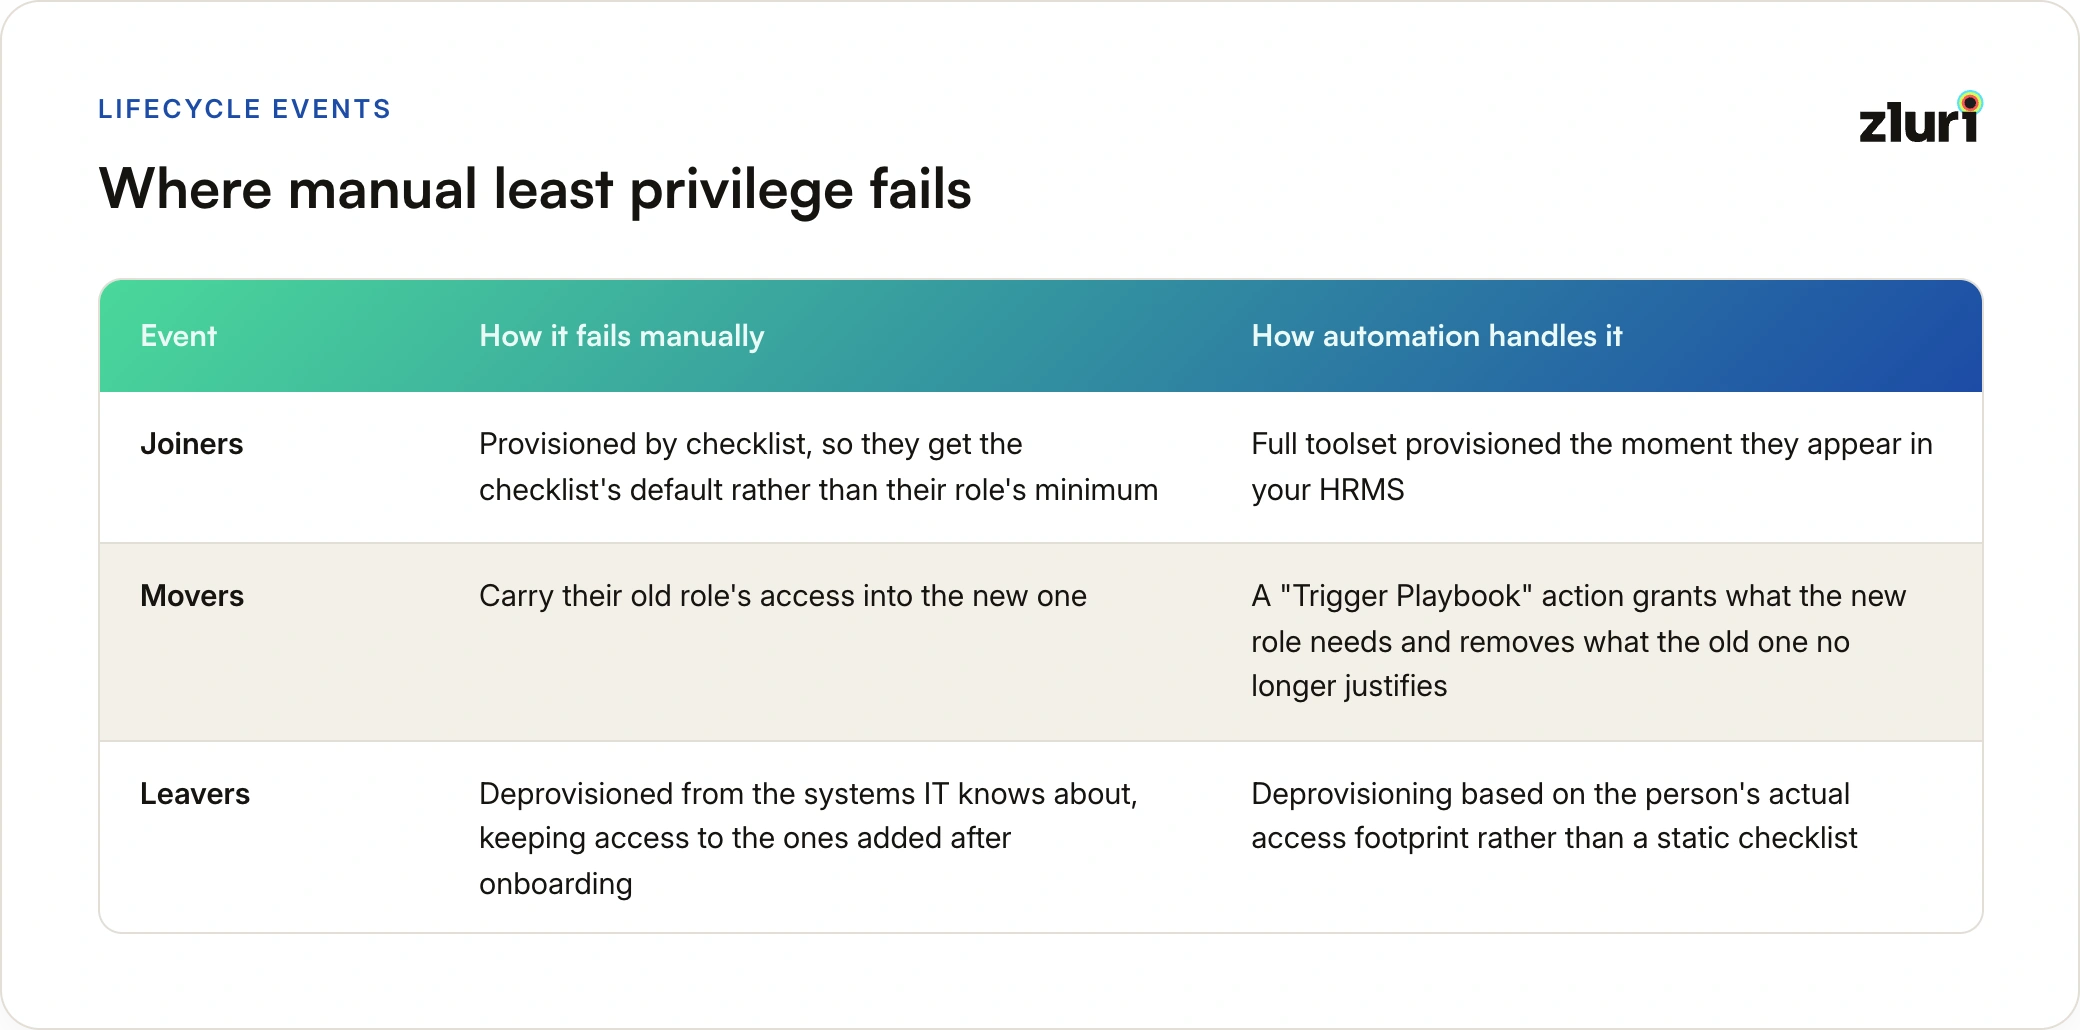
- Joiners get provisioned by checklist, which means they get the checklist's default rather than their role's minimum.
- Movers carry their old role's access into the new one, because organizations are good at granting what a new role needs and poor at removing what the old one had. Movers are the least-managed event in most identity programs, and the one that produces the most PHI exposure over time.
- Leavers get deprovisioned from the systems IT knows about, and keep access to the ones added after onboarding.
Zluri's Access Management handles this through automation rules: define a condition once (role, department, location, or another attribute) and the system applies it across every connected application, rather than requiring manual configuration per app. A rule can be as specific as granting access only to users in a given region, or as standard as provisioning a new hire's full toolset the moment they appear in your HRMS, with sync as fast as instant for platforms like BambooHR, Google Workspace, Azure AD, and Okta. This is HR-driven provisioning: the HR record is the trigger, so access follows the organization's actual decisions rather than a ticket someone remembered to raise.
Role changes work the same way. A single automation rule with a "Trigger Playbook" action carries a mover event (a department transfer, a promotion, a relocation) through every affected system, granting what the new role needs and removing what the old one no longer justifies. Offboarding runs identically in reverse, deprovisioning based on the person's actual access footprint rather than a static checklist that misses tools added after onboarding. Our map of deprovisioning paths in Zluri covers the full set of triggers.
Least privilege that depends on someone remembering to configure it per app, per role change, is a policy. Least privilege applied by rule the moment the HR record changes is a control.
4. Run Periodic Access Reviews to Catch What Automation Misses
Automation handles access at the moment of change. Reviews catch what accumulates between changes.
That includes access that was correct when granted but no longer matches the role, accounts that should have been caught by an automation rule but weren't (because the HR data was wrong, or the application wasn't connected yet), and access that was granted outside any rule: a manual exception, a self-service sign-up, a vendor account no one re-examined. HIPAA doesn't specify a review frequency, so the cadence is yours to define and defend (our guide to how often access reviews should happen covers the tiering); the PHI classification from step one is the natural basis for tiering it, with the highest-exposure applications reviewed most often.
An effective review process lets you select the PHI-handling applications in scope, pull current access automatically from the source systems, and surface anomalies: unauthorized users, former employees or contractors who still hold permissions, access with no login in months, and access no one can justify against the person's current role. For PHI, the review has to operate at the role level, not just the application level. Confirming that a clinician "has access to the EHR" tells an auditor nothing about whether that access was minimum necessary. The reviewer needs to see the role, and the review needs to offer a downgrade as a decision, not just approve or revoke. Our guide to least privilege in SaaS access reviews covers why the role and license dimensions matter as much as the access itself.
Zluri's Access Reviews workflow does this and lets reviewers trigger deprovisioning or downgrade actions directly from the findings, through closed-loop remediation that executes the change and logs what was reviewed, what was decided, and what action was taken.
One diagnostic worth building in: if a review consistently surfaces a high volume of anomalies, that's a signal the underlying access rules need tightening, not just that this cycle's findings need remediating. A review that finds the same class of excess every quarter is reporting a provisioning problem.
What This Looks Like as Evidence
An OCR audit doesn't ask whether you believe in zero trust. It asks for proof.
Specifically: who has access to PHI right now, what justified that access, when it was last reviewed, and what happened when the review found something wrong. The prose version of how each mechanic generates its piece of that proof, then the table: classification produces the scope record; per-application boundaries produce per-system access logs; automated lifecycle rules produce the grant-and-revoke trail tied to HR events; and periodic reviews produce decision records with justifications and remediation logs.

The point of automating the mechanics isn't only that they run faster. It's that the evidence generates continuously, as a by-product of the controls operating, instead of being reconstructed in a scramble before the audit. The access review audittests auditors run (sampling decisions, tracing revocations to execution, checking reviewer independence) all depend on that record existing before anyone asks for it. And the gap between a documented policy and an operating control is exactly where HIPAA access violations tend to originate.
Where Zluri Fits
Zluri applies zero trust's core principle, verify before granting, at the identity layer across the applications where PHI actually lives.
Access Management enforces least privilege through automation rules that apply role, department, and attribute conditions across every connected PHI-handling application, without manual configuration per app or per role change, and carries joiner, mover, and leaver events through every affected system from the HR trigger. Access Reviews closes the loop with periodic, role-level review of PHI access, remediation that executes from the review decision, and the timestamped record of who reviewed what, what they decided, and what changed as a result.
Together they turn zero trust from a stated philosophy into the thing HIPAA actually asks for: evidence that access to PHI is limited to what each role needs, verified continuously, and corrected when it drifts. For how the "never trust, always verify" principle applies to identity specifically, see how Zluri implements zero trust for identity. For the broader healthcare governance picture, our guide to identity governance in healthcare covers the full program.
Frequently Asked Questions
Does zero trust replace HIPAA's other required safeguards?
No. Zero trust strengthens the technical safeguards tied to access control, but HIPAA still requires physical safeguards (such as restricted workstation access) and administrative safeguards (such as breach notification processes) that zero trust doesn't cover on its own.
Is zero trust the same as least privilege?
They're related but not identical. Least privilege defines how much access a role should have. Zero trust is the broader principle that no request, regardless of source, is trusted by default, which includes continuously re-verifying access rather than granting it once and assuming it stays valid. Least privilege is one of the things zero trust enforces.
How does zero trust handle third parties who need PHI access, like billing vendors?
The same way it handles internal users: access scoped to exactly what the vendor's role requires, verified on every request, and included in the same periodic review cycle as internal accounts. A vendor account with standing, unreviewed access is one of the more common gaps in otherwise strong access control programs, and it's a gap OCR auditors know to look for.
How often should PHI access be reviewed under a zero trust model?
HIPAA doesn't name a frequency, so the organization defines and justifies one. A defensible approach tiers cadence by PHI exposure: the highest-sensitivity applications reviewed monthly or on every role change, standard PHI-handling systems quarterly, with event-driven reviews triggered by transfers, departures, and new privileged grants in between.
Can zero trust access control be implemented without automation?
Technically yes, but it rarely holds up past a small number of applications. Manually verifying and re-verifying access across dozens of PHI-handling systems, while keeping it current through every role change, is the exact workload automation rules are built to remove. Without automation, the model usually degrades into a documented policy that the actual access doesn't reflect.
What evidence does an OCR auditor expect for access control?
Proof of who currently has access to PHI, what justified that access, when it was last reviewed, by whom, and what action followed if the review found a problem. Automated provisioning and deprovisioning tied to HR events, plus periodic reviews with decision records and remediation logs, generate that evidence continuously rather than requiring it to be reconstructed before an audit.










